Showing posts with label anemia. Show all posts

Friday, November 1, 2013

Avoidable Maternal Death

We had a maternal death today at NJH. 

The major aspect was that the death could have been avoided if somebody had identified risk factors, taken extra precautions and had been a bit more careful.


FmB, 22 year old mother of two came to us about 3 hours after delivering a healthy baby in a health facility about 5 miles from our place. She was gasping with a feeble heart as she was wheeled it. In addition, she was papery pale. There was nothing left for us to do. There was no blood in her veins. All of it had bled out. 

Although we had her intubated and pumped her with ionotropes, she did not respond.

FmB had been bleeding after the delivery. The care-givers had been giving her some injections to stop the bleeding. 

Unfortunately, by the time they realized that it could be fatal, it was too late. 

FmB had come to us couple of times for ante-natal care. Her hemoglobin was 8 gm% about a month back. I can't find much reason that it would have increased much although she was on regular Iron tablets. 

I'm sure that her care provider during the delivery had much idea about her anemia. There was no documentation of hemoglobin having been done elsewhere. 

Of course, if she had come to NJH, she would have ended up getting a repeat hemoglobin and a request to arrange one pint blood if the hemoglobin was below 9 gm%. 

Of course, I've had one of my dear colleagues in a sister hospital debating upon how one could manage conservatively without blood transfusion. In a situation where there is readily available blood, I may not arrange the one pint blood. 

And if UDBT was legal, this would be one classic case which would have made it if she had come in about half an hour earlier. 

To sum it up . . . FmB's death was a wake-up call for quite a few of us attending to her. A very normal process of delivering a baby ending up in a tragedy . . .

No eclampsia or rupture uterus . . . maybe, the uterus refused to contract . . . or a bad birth canal injury . . .

But, at the end of the day, a preventable maternal death . . . 

I feel sad for the husband and two very young daughters, the first one, just completing 2 years of age and the second one, born today . . .


Tuesday, June 4, 2013

Thru' the valley of death


RD was a very non-suspecting high risk antenatal patient. The issue was with her hemoglobin. It never crossed 8 gm%.

However, considering her family’s financial situation, wehad decided to take her at NJH for delivering her baby by Cesarian section. This was her second baby and her first baby also was delivered by Cesarian section.

None of us had any inkling of the crisis we were going to face.

She had a blood transfusion before the surgery. Unfortunately, the doctor who operated did not do a repeat hemoglobin value before taking her in for surgery. Per-operatively, she developed a reaction to the blood transfusion. There was nothing much of a problem.

After the surgery, she was comfortable. However, there was a nagging issue. She was not maintaining her saturation. However, the saturations became normal when oxygen was given. A hemoglobin done on her turned up a value of 6.6 gm%.

Alarm bells started to ring on my head. We decided to wait overnight.

The decision turned out to be almost fatal. She started to have breathlessness in the night. Her saturations took a dip for the worse. She was going into pulmonary edema.

By morning, she was in the ventilator. But, she was also putting out pink frothy sputum. We had to give about 1 gm of Furosemide over the first 24 hours to control the pulmonary edema.

By God’s grace, she responded well to treatment.

And she got discharged last Sunday, exactly 7 days after her surgery.

However, RD’s incident has prompted me to put in strict control on hemoglobin values of our prospective patients. Anemia is quite prevalent in our part of the country. It is not very common for a pregnant lady to have a hemoglobin of above 10 gm%.


Meanwhile, the debate on anemia always cause me to wonder if we have some form of a blood dyscrasia in our part of the country, which is not yet diagnosed. 


Two Maternal Deaths


Yesterday, we lost SHD. She was sick, but stable, while I saw her in the morning. I was in outpatient department, when I got a call that she had a cardiac arrest. The problem was that it was some time after that she had the arrest and the nurses could not find a doctor in the immediate vicinity to come and help.

I knew that there was no point in attempting a resuscitation. However, we tried the routine procedures. . . . but without any success.

And then we lost LD 4 days back. Couple of days after the surgery, she went into florid septicemia. She was being ventilated. And she started to pour out pus from the lungs, abdominal drain and also from her vagina. The relatives requested that we do not do anything heroic. Obviously, they were poor and was slowly noticing how the expenses went up.

After quite a long time, I withdrew life support for a young life.

Then, there was PD. A primi in her last weeks of pregnancy. She had not been doing well since about 2 weeks. Yes, 2 weeks. And she was taken from hospital to hospital. She was gasping as she was wheeled into NJH three days back. In fact, the relatives told us that she has been gasping for breath since 2 days. Dr. Johnson, our doctor on duty realised that there was nothing much he could do.

2 gm% was her hemoglobin. By the time, he found out a donor, she was dead.


So, we had 2 maternal deaths due to anemia last week. I wonder how long it will take for our guys in the thrones of power to realise that such preventable deaths are a major deterrent to development.

There is now one more near maternal miss patient in acute care. BDD, whom I wrote about in the last post has been weaned off the ventilator today morning. Kindly pray that BDD would recover completely.  


Monday, May 27, 2013

Tale of 2 Anaemic Patients


Yesterday was my first Sunday first call duty of the year 2013.

Early morning, I was informed of a very complicated patient in the labour room. LD, a 26 year old lady has been in labour since Saturday early morning. She has been running from hospital to hospital trying to get some help. The problem was that she had a hemoglobin of 6 gm% and nobody was willing to take her. To make matters complicated she had been given injection pitocin elsewhere. She had a pregnancy couple of years back. The baby had died just after childbirth after she had attempted a home delivery.

She was O positive. Dr. Johnson tried to arrange some staff to donate when she reached late night on Saturday. Unfortunately, we do not have many staff with O positive blood group. There was only one option. Either the patient had to be referred or we had to do the surgery with a consent to do without blood which was not a easy choice. The family having had visited quite a few  hospitals before entering NJH had already spent quite a lot of money on her ‘treatment’. So, the question of going to Ranchi was totally out of question.

However, we decided to wait for blood to come.

It came . . . by around 11 am on Sunday morning. It had been a full 33 hours since she had been in labour. And she was into obstructed labour.

I opened and found the worst I had feared. The uterus had ruptured. The baby was alive but quite sick. The endometrium and placenta was grossly stained with meconium. The baby died by evening. LD lost quite a lot of blood. She is on the ventilator and fighting for her life.

As we were doing LD’s Cesarian section, rather laparotomy, in came SeD.

Frighteningly, SeD also had a history similar to LD.

SeD was brought by her parents. Her father, a wizened old man who had quite a lot of creases on his face was a sorry figure.

The history . . . SeD had also been in labour since the previous day. The family had been to many hospitals. She was also told that her hemoglobin is 6 gm%. And her baby was in an abnormal position. The nurses could not get the fetal heart. I was in a hurry.

I told them to push SeD into the ultrasound. I had a cursory glance at the fetus. The heartbeat was going strong and was a footling breech. No other choice than to do a Cesarian section.

I did not think twice. She was B positive. I send word to 2 of our staff requesting to donate blood. SeD was having very strong uterine contractions. I did not want SeD to end up with the same outcome as LD. Ebez George, our Project Officer and Dr. Basil, our Dentist were were happy to donate.

We did the Cesarian in no time. To my surprise, SeD had a twin pregnancy. Mother and babies are doing well. I had missed that in my ultrasound screening.

I wondered why we did not have a staff with O positive blood who could help LD and her baby. They would have done better. The baby would have been alive.

But, a terrible thing happened later. I went to see SeD’s father. He had narrated to me SeD’s sad story. SeD had also delivered 2 years back, but the baby had died soon after her home birth. When SeD got into her present pregnancy, SeD’s husband took her and left at her parent’s home and told them not to send her back if she did not have a live baby this time.

I was congratulating myself as I saw SeD’s father standing at a distance and was happy that I had good news.

I could only watch with horror the pain that SeD’s father’s voice echoed when he came to know that his daughter had delivered twin girl babies. The creases on his face becoming deeper as he pondered aloud, ‘Doctor saab, I wonder if SeD’s husband would come to take her back with the 2 girl babies’.


Please pray that LD would recover well and SeD’s husband feels proud to be the father of 2 daughters.

Sunday, April 28, 2013

Neglected Hand . . . Need Help

I need help to manage a patient.

This 45 year old lady came to us with a very bad ulcer of her left wrist. And it is stinking very bad. It seems that there are maggots inside. 


The X-Ray shows dislocation of the metatarsophalangeal and distal interphalangeal joints of the thumb. There appears to be gas gangrene too. 

We tried our best to send them off to a higher centre. They are only willing to go home if nothing can be done here. 

The additional challenge is that she has a hemoglobin of 5 gm%. And an ESR of 150 mm/hr. And no evidence of diabetes. 

My plan is to do an amputation as soon as we get couple of pints of blood. 

Any other choice . . . I would appreciate responses . . . 

Thursday, October 18, 2012

Anemia . . . ? Lack of Evidence

3 days before I started on my holiday, we had a pregnant lady at term who was bleeding from the morning come to us sometime in the evening . . .  and die couple of hours later. Dr Shishir who was on duty called me to report the maternal death. The history was appalling. The lady should never have died.


She had her routine antenatal care. Her hemoglobin done few weeks back showed 8 gm%. No ultrasounds were done. She was on oral iron. She had started to bleed in the morning. The relatives had taken her to the district hospital. She was there for quite a long time. The relatives were not sure what was done. Later they took her to a private hospital from where she was referred here. 

We could not measure any blood pressure on her and there was no pulse. She was white like paper. Hemoglobin came as 5 gm%. I'm sure it must have been lesser. There were no relatives to give her blood. We tried our staff. Although, the blood group was a common one . . .there was nobody who was fit to give blood . . . couple of them were sick, others had given recently. 

Her blood pressure or pulse never came . . . without blood, there was no option. She died . . .


Talking about her hemoglobin of 8 gm%, it is not an uncommon thing at NJH. We routinely see hemoglobin values of 8 and even lesser. The reason I write is the recent discussions I had with few of my friends and an article I read today about the use of parenteral iron in situations such as ours. 

If we keep the cut off of 11 gm% to diagnose anaemia in NJH, I'm sure we'll diagnose almost 100% of our pregnant women anaemic. Values of 9-10 is the highest you will find here. Almost all studies done at many places in India gives the prevalence of anaemia in pregnancy as something between 30% and 100%. 

So, I was quite surprised when I read in the article mentioned above that the patient Ahmedbi whose hemoglobin was 9.8 gm% got a drip of Iron-Sucrose. Well, I can imagine the justification of the doctors who have started doing this in spite of not much evidence for such a practice. 

Anybody who has taken the Iron tablets given by the government would vouch for how unpalatable it is. And to have it during pregnancy is something which many a pregnant lady would not really like. Over my clinical practice, it has been quite common to have patients confess that they have not taken their prescribed medicines and pregnant women not taking their Iron and Calcium form a major chunk. 

And even when they take it, there are other issues involved. I've somehow come to believe in the theory of the chronic malnourished state. I remember someone talking about it . . . but can't remember who it was. The theory is that in many of the impoverished regions of the world, the chronic state of malnourishment results in the body being adapted to function with a below optimum level of nutritional states. Which ultimately results in a poor absorption even in a situation when there is adequate nutrition available.

Otherwise, I cannot explain how in NJH we see so many people from rural areas who would have been labelled terribly sick in a tertiary hospital elsewhere survive tough surgeries and major illnesses like malaria, enteric fever etc. 

The chronic malnourished state continues even the lady becomes pregnant and no amount of iron and vitamin B12 pushed down the gut brings any change in the hemoglobin levels. 

Well, I'm sure that this would need to be researched well before we can draw conclusions. 

One more reason why I suspect a faulty absorption of nutrients in states of chronic malnutrition. We see quite a lot of patients with clinical features suggestive of Cyanocobalamine deficiency who do not respond to oral Vit B12 . . . but respond well to Vit B 12 Injection. I do not expect a high prevalence of Intrinsic Factor deficiency in the population . . .  Well, another explanation is the low IF values in people with chronic malnutrition states. 

Whatever it is . . . one thing have I realised. The knowledge we have about something as simple as anaemia is quite limited . . . leave alone complex diseases like cancer . . . 

So, anybody interested in research in this area . . . 

The parting shot . .. ... Sometimes I wonder, in a country like India . . . even evidence and scientific explanations are sometimes of no use. It might surprise you . . . We do not have provision of free Iron and Folic Acid tablets for our Antenatal patients . . . This is when we have enough of evidence about how Iron and Folic Acid tablets could be the lifeline to Antenatal patients . . . 

Preventing maternal deaths as the one mentioned in this post . . We do not have blood banks where there is round the clock availability of blood. And this holds true for the 4 million population in catchment population . . . Well, that is a post for another day . . . 

Monday, August 20, 2012

Pharmaceuticals - The Paradoxes in Indian Healthcare . . . Part 1

We are all well aware of how sick our system of healthcare is. While for the rich and the famous, it is nothing much of a major concern . . . for the middle class and the poor, healthcare is a major issue of concern.

However, what concerns me are reasons for the government being only hardly bothered about what sort of healthcare the common man has access to. One on side, we are proud of how good we are with tertiary care and we are looked upon as one of the major spots for health-tourism. We have states such as Tamil Nadu who are looking at up scaling of cadaver organ donation whereas on the other side, we've states where something as basic as availability of blood is a major issue.


I'm a bit concerned about the sort of media attention that issues such as cadaver organ donation, celebrity health issues garner compared to the status of basic public health care in the country. One issue which has been sort of been ignored is the state of tuberculosis in the country. I've taken up the issue many a time in my blog.

Well, you may say that we have the Revised National Tuberculosis Control Programme, a world award winning public health program which has won accolades at many a venue.

I take the issue of Tuberculosis today on account of one patient whom Titus saw in Outpatient today.

SDS was a unmarried 26 year old man who hailed from a village within 10 kms of our hospital. Hailing from a rich family, SD had been diagnosed to have Type 1 Diabetes Mellitus 7 years back. Then he had been diagnosed to have tuberculosis about 4 years back.

The sad aspect was that he did not access the free government tuberculosis drugs. He had quite a large file of his medicine prescriptions. It was quite a sad array of paper work he carried around.

Initially, he was started off only with Rifampicin and Isoniazid. Nobody was there to monitor his treatment. He took medicines for about 2 months and he left treatment when he started to feel better. Then, he became sick again. He went elsewhere and was started on medications again . . .

Unfortunately, by early 2010, someone had sent his sputum for culture testing. Below is the report.


But, I was in for a shock when I saw the prescription from the 'tuberculosis specialist'. All protocols of Multidrug Resistant Tuberculosis was thrown to the wind. It's more than 30 months. He's still on treatment.

And the worst shocker of all . . . He never had a sputum AFB done. . . of course, there was a sputum culture done about 2 years after the first diagnosis.


Well, you could blame SDS for not taking interest in the government run RNTCP programme.

But, I wonder why anti-TB drugs of all combinations and dosages are available in the open market when there is a government run programme to combat tuberculosis.

To make matters worse, there are quite a large majority of doctors who openly tell their patients that government medicines are of no good. SDS was told the same thing by every doctor whom he accessed for treatment.

Recently, the government has come out with an order on generic drugs. The pharmaceutical industry has already launched an all out cold war against this. They have even invented a term for generic drugs - 'unethical drugs'. And the branded drugs are called 'Ethical drugs'. So much to educate the common man on the terminologies of drugs.

Well, it was quite incidental that I came to find out that there is no Iron tablets in the Primary Health Centres around our place. But, Iron capsules are available in the Pharmacy shops and they were doing great business. Even, we are doing great business with Iron capsules. I remember that during my stint elsewhere in the South, the Medical Representatives were all out 'educating' us on how unpalatable the Iron tablets are compared to their 'double coated chocolate flavoured' and of course expensive Iron capsules.

SDS is most probably going to pay for his ignorance of the existence of a government scheme which would have monitored his drug compliance and disease progression. Now, he is getting a MDRTB treatment protocol which is totally out of line from what he should be getting.

I'm sure that this is part of the influence of private players who are very well aware of the inexhaustible gold mine of profits made in the name of healthcare. It is sad that the government is not realising the folly it is in by allowing such a back-door entry for private players in healthcare. The influence looks subtle, but the consequences are going to be disastrous for the common man.

The government order on making generic drugs freely available is a decision in the right direction. I was quite encouraged to see the 'Generic drug store' in the Latehar district hospital during a recent visit. I'm sure that the private drug companies and retailers would go on an all out war against it, at least indirectly if not directly. More initiatives such as these are necessary if the common man has to regain his confidence on public healthcare.

However, it is going to be quite a long journey for all of us who are mooting for a full fledged robust public healthcare. The question is how many of us are going to continue fighting to see a day when that happens.

Thursday, June 21, 2012

Rose Trampled . . . The Indian Woman . . .

It has been busy at NJH since the last rains. However, the monsoon rains has made life easier as the weather has cooled. For me, it has been all the more busy as I prepare for the annual meetings of the organization. After the spate of patients with eclampsia last week, I had been expecting a lighter week. Moreover, the rains will keep the rural populace busy with agriculture work. 


As I ensured that the Outpatient Department was functioning smoothly for the early morning rush, there was this young man trying to get my attention. He told me that he has been by someone I knew in Latehar. The next thing I know is that he puts a mobile onto my ear saying that the person I knew wanted to talk to me. It was nothing new. The young man had brought someone whom I should see. 


The young man took me to the patient. A young lady, obviously pregnant - but severely pale, with a swollen face and legs which looked as if she had filariasis of both the legs. And she could hardly sit. 


They had couple of prescriptions from elsewhere. Both of them were illegible to me.


The history - We'll call this lady AD. AD had become pregnant for the second time while her first child was still not one year old. She did not have a date from which we could calculate her expected date of delivery. She had not been doing well for the last couple of weeks. She was in her husband's house - but her husband was away; working in Bangalore. She lived with her in-laws and her daughter. 


Without much of an examination - the diagnosis was obvious. Severe anemia, malnutrition and probably pre-eclampsia. And most probably a baby with intra-uterine growth retardation. I scribbled off some investigations and send her to the ward for admission and observation. 


I called the young man, who happened to be AD's brother and asked further about how she could be so malnourished. It seems that there was hardly anything to eat in the family. It was a hand to mouth existence. He was sad that she was married into this family. It seemed that AD's husband also did not care much for the family. And the fact that the first child was a girl did not make things easy. 


As we talked, I received information that her blood pressure is on the higher side. Initially, it looked normal. However, they had been elsewhere before reaching here. Then the investigations came. Hemoglobin of 6 gm%, Serum albumin of 2 gm%, Urine albumin of 2+ . . . Well, I did not require anything more. To top it all, a blood group of AB positive . . .


I told him about our limitations. She needed blood . . .There was the impending eclampsia round the corner. She was terribly malnourished. . . I gave him all the options. . . The problem was the costs involved . . .I talked to this acquaintance in Latehar. He told me not to take any risks . . . And AD's brother was also not ready to take any risks . . . After some time, they were off to Ranchi . . . 


I wonder if AD's husband's family had somehow found out that the fetus was a girl. Or was it just poverty. It was difficult to say . . . 


It is terrible. A country where goddesses are venerated to enormous proportions - the state of the girl child and the woman is in doldrums . . . The same neglect was seen in the last patient about whom I mentioned in my last blog . . . The welfare of the lady or the girls in the house seems to be the last concern . . . 


And what do we have . . . Pregnant women with severe anemia . . . giving birth to underweight babies . . .and if they are girl babies, they are all the more neglected. Growing up in a suppressed environment where they are made to believe that they are the 'flowers in someone's garden', they yearn for the day of their wedding after which they can redeem themselves by giving birth to a boy child . . .


Now, all this - if they make it alive through the different phases of their life's journey. They are lucky if a neighbourhood ultrasonologist do not make an early diagnosis of a girl fetus and inform it to the relatives. And then, all the childhood illnesses which could have killed her had she not had God watching from above. . . To suffer the taunts and evils of eve-teasing and a risk of being physically abused. . .  Then comes marriage . . . the undernourished body strained into conceiving and nourishing another human being . . . 


I'm sure that the Indira Gandhis, Pratibha Patils, Mamta Banerjees and Jayalalithas are just not representative of what the state of the Indian woman is. . . Many of the time, we trumpet about the great women leaders that we've had starting all the way from the Rani of Jhansi. . . I feel that all of that is of no use unless the average Indian woman especially in our slums and villages are given decent care and respect . . . 


I pray the AD would have a non-complicated delivery and post-partum period. It is a very costly and dangerous path that she is on . . . I wish that AD's brother would have the wisdom to treat his wife in a better manner . . . May wisdom dawn on the menfolk that they treat their wives and daughters better . . .

Tuesday, April 24, 2012

2 Happy Families . . . Could have been tragedies . . .

Over the last week, in addition to the tragedy of 3 members of a single family getting burnt, we did have our moments of joy. . .


The first reason for the same was SD1. SD1 came about 10 days back in a terrible state. It was SD1's first pregnancy. There was no antenatal check up. She had turned up at the neighbouring district hospital after being in labour at home for some time. It was sometime before the people there realised that SD1 looked a high risk case.


SD1 had a hemoglobin of 5 gm%. On per vaginal examination, the cervix was edematous with dilatation of 5 cms and there was meconium pouring out. I was in a fix. The referral letter mentioned that SD1 is being referred to Ranchi. We needed blood. There was only one bystander.


I was thankful when the blood matched. But, one pint was never enough. I was sure that the hemoglobin would be lesser than 5 gm%. However, we had to do the surgery. Otherwise, we risked having a rupture uterus and a dead baby.


We went ahead with the surgery. The baby was sick. But, he somehow pulled through. The bystanders were  quite fast is arranging two more pints of blood. It was quite a relief when SD1 recovered soon to be discharged.


The challenge for us was the bill. Because it involved 5 blood transfusions and neonatal care, the total bill was around 20,000 INR. The family was too poor. It did not need much convincing that they would not be able to afford even half of this bill. They paid about 10,000 INR. The rest went as charity. It is a burden for the hospital. But, considering our vision and mission, we have to make such concessions. . . 


The next patient was SD2. Married for 14 years, the family did not have issues. The interesting aspect was that she had a whopping 8 abortions. And the saddest part was that she did not take much interest to do any antenatal check up during the present pregnancy. The delivery was uneventful. It was a pleasure to watch the joy of the family as they adored the new arrival. 


The last one was 2 days back. SS had come with usual labour pains after an uneventful antenatal period. On arrival in labour room, Dr Johnson diagnosed a breech presentation. Since she was a multi, we did not anticipate much problems. But, as soon as the breech was out, Dr Johnson was sure that there was one more baby inside. And yes, she had a surprise twin delivery to add to her already large family of 3 children. 


All the 3 deliveries, especially the first two could have ended up as tragedies. We are thankful that all the babies and mothers are doing well.


Over the last 2 weeks, the 'marriage season' has started in this region. It is very hilarious. Everything revolves around the weddings. Almost everybody in the ward requests for a discharge citing excuse to attend a wedding or to get married . . . We expect quite complicated cases to come in during this period. In addition, we have students from the Christian Medical College, Vellore visiting us for the next 2 weeks. Do continue to follow the blog . . . there should be interesting posts continuing . . . 

Monday, February 6, 2012

Blood . . . rarest commodity . . .

Some time back I had put in a terrible snap of a blood bag which relatives of one of our patients had brought from our nearest district headquarters. 


Yesterday, we had 2 patients who had come in with hemoglobin values of around 5 gm%. 


The first patient, RK was the mother of 4 children and she was pregnant at 7 months gestation. She was from quite far away. She had suddenly started to bleed early morning. By the time she reached here sometime late afternoon, she was quite pale with no fetal heartbeat audible. Her hemoglobin was around 5.8 gm%. I informed the relatives that we could not do much without at least a couple of pints of blood. 


That was when the husband informed us that the unavailability of blood in the district headquarters was the reason for her being referred to NJH. In fact, the relatives wanted to know if they could take the patient to Ranchi. I was relieved - but later realized that she was continuing to bleed and the vitals were going down. But, without blood I did not have any choice. 


In the available circumstances, doing the 135 kilometer journey through bad roads was the best choice that RK and her family had. RK's relatives were well off and it was not quite difficult for them to take a decision to move ahead. I ensured that RK had two lines going in with intravenous fluids. 


As soon as RK left, came the next one. SD, another multiparous lady with bleeding since early morning. Contrary to RK, SD's family was very poor. It had taken them quite a long time to arrange transport and other arrangements to make it to NJH. SD had another episode of bleeding earlier last month. However, it had subsided within few minutes. I told the family of my predicament of not having blood readily available. 


The family expressed their inability to go any further. The husband told me, 'Sir, please do what you can. Even if the baby dies, please save the mother.' The blood results came. Hemoglobin of 5.3 gm% and the blood group was not matching with that of any of the relatives. It was quite late into the night and the relatives informed me that they would go to arrange blood as soon as it is daylight. I told them that it is a very risky plan. If she bleeds, we've had it. 


Meanwhile, we did an ultrasound. It was a low lying posterior placenta with abruption. The baby was alive. I could only pray that she would not bleed. Soon, she was into her labour pains. I was surprised that she did not have any bleeding. Within couple of hours, the baby was on the way. She delivered a dead baby. Thankfully, she did not bleed much. 


Blood transfusion facilities are a premium in almost all parts of rural areas of third world countries. In emergency cases, we keep few blood bags where we directly bleed for donation. It is illegal - but we do it so that lives can be saved. 


The present policies of blood donation are quite archaic and it becomes quite difficult in difficult areas such as ours. And since the last few days, we had run out of blood bags . . .  We are yet to get them . . . We could have managed RK if we had at least couple of blood bags, if not given her a better chance of surviving the journey to Ranchi . . . 


Tuesday, October 18, 2011

Maternal Health Care in Palamu - Red letter day

Today was a red letter day in the history of maternal health care of our region.


The UNICEF along with the district health authorities of Palamu district had arranged for a training session on Facility Based Maternal Death Review. I understand that soon there would also be efforts taken for training grassroot workers on Community Based Maternal Death Review.


Mr Prabodh Kujur and myself represented NJH as we have quite a large burden of adverse maternal events including maternal mortality. Over the last 1 year, we calculated about 20 maternal deaths within the facility. This excludes at least 5 patients who were brought dead.


One of the key messages which was conveyed to all the doctors who came was about the absence of a blame factor in the whole exercise. Many a time, adverse health events are not reported because of a fear of punishment. I was very glad that the message was conveyed well.


As I sat there, images of mothers who died or almost died, those who ended up with lifelong complications and dead babies flashed before me.


I remembered AB's baby who just made it whereas she should have been referred faster. BD, whose life has turned for the worse was a poignant face whom I would remember for the rest of my life. One of the major finding I would expect from the reviews is the strong association between malnutrition and anemia. 


The mental stress that KD's family endured was still fresh in my mind. Our experiences with patients like RD, who lost her baby or SD, for whom we had to intervene heroically have already taught us that the delay in taking the decision to go to the healthcare provider and the delay in implementing the decision is quite costly in the lives of mothers and newborn. I'm certain that this is going to be one of the major learning in this exercise.


I'm excited about the whole excercise. We look forward to a time of learning and understanding determinants influencing maternal health care in this region during the maternal death review meetings at the institutional and district level.


More than that we look forward to a period in our surrounding communities where pregnancy is more safe whereby families will cherish and enjoy motherhood which would be the ultimate aim of such an exercise.

Monday, September 19, 2011

Anemia and Malnutrition

Over the last 1 month, we have been facing the brunt of morbidity that anemia can cause in our patients. Today (19th September, 2011), I had to face the havoc it could play in our patient’s lives. We ultimately end up taking uncalled risks in the management of our patients.

Anemia in obstetric patients in this part of the country has always been a constant problem. Over the last 2 weeks, we had 6 bad wound infections after Cesarian section. Overall, our practices of sterile techniques and patient management protocols are quite robust to ward off any possibility of infection.

The constant feature we saw in each of the 6 wound infections was a pattern of low hemoglobin associated with a history of having been handled elsewhere. It is quite easy to find excuses and shift the blame to something else. Of course, I’ve already started a process of reviewing our processes and ensured that fumigations are done at the necessary places as well as tested the autoclaving processes.

In addition to the low hemoglobin, we’ve discovered something else too. And that is the low serum protein levels in such patients. Of course, before I come to a conclusion, we need to compare it with the other patients who do not develop wound infections.

Nevertheless, I just wanted to put in this post something which I’ve been thinking for quite a long time. I suspect that most of our patients are chronically malnourished. When I look at my anemic patients, many of them have told me of having taken their iron tablets. But, when I ask their dietary practices, I get very terrible replies. For most of them, their basic diet is rice with a little dal which becomes more watery as you become poorer.

Basically, none of these people have much of any protein in their diets. Well, if you know medical biochemistry, iron transport occurs in our body through protein substances called ferritin and transferrin. When people have such a protein deficient diet, how can you expect their bodies to make transferring and ferritin which are very much essential in the absorption, transfer and storage of iron?

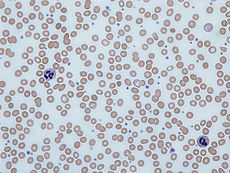
One more facet of anemia which has been quite known to quite a number of clinicians but quite ignored in clinical teaching is the role played by Vitamin B12 and Folic Acid in the synthesis of red blood cells. After Angel joined work, I’ve been encouraging my colleagues to send peripheral blood smears of patients who have anemia as well as tingling/burning sensation or numbness of the limbs. Angel has been reporting macrocytosis, and hypersegmented neutrophils which is very much suggestive of Vitamin B12 deficiency.

I wish we could do an epidemiological study into this aspect of anemia. I understand that I could be wrong – but there is enough evidence to warrant a proper look into this by the scientific community. There are quite a lot of things which I suspect – there could be a Intrinsic Factor deficiency in the community, the diet could be poor in Vitamin B12 deficiency, there may be inhibitors of the absorption of Vitamin B12… However, there is a common denominator to all this – and that is the lack of a balanced diet in the community.

The lack of a balanced diet is very much linked to the issue of food security. The nutrition is quite skewed towards the carbohydrates and the fats. Proteins are a definite no-no in most of the diets which I’ve experienced in the communities here. And one more matter of concern is the lack use of vegetables in the diets here in spite of the local cultivation and availability of vegetables.

I’ve always felt that the lack of Public Distribution System has played havoc in the dietary patterns of our communities and patients like the one I described in my earlier post reinforce this. When I look back at my childhood in Kerala, the Public Distribution System played a very significant role in ensuring that no family went to bed without food. If it is true that the chronic malnutrition which is being purported as a cause of the various deficiencies which we commonly see in the rural communities, there is a strong case from the healthcare research community to strongly establish (in some places re-establish) the Public Distribution System in every nook and corner of the country.

Monday diary

We start Mondays in NJH with much anticipation and preparedness. Usually, they are very busy and it would be very difficult to find any of us sitting doing nothing. I knew that today was going to be tougher than usual as Dr Nandamani who was on duty on Sunday was running a very high fever with body pain and Dr Johnson was on leave.

As soon I finished the rounds in the Maternity Ward and before I started rounds in the Male ward, I managed to peep into the OPD and was surprised to find it quite empty for a Monday morning. I took things a bit lightly and did a very relaxed round in the Acute Care Unit and the Male Ward.

Well, silly me. It was just the calm before the storm. As soon as I finished Male ward rounds, I got a call from Dr. Nandamani requesting me to review a patient in OPD. KD who had a LSCS about a month back had come with pus pouring out of her vagina and pieces of catgut too. The patient was otherwise doing fine. She had come quite sick for her delivery. She was unconscious and having continuous seizures following which we had do an emergency cesarian section. She was in the ventilator for 4 days. The relatives had given up hope. Somehow, she had lived. I asked for an ultrasound. She was quite pale. I’m yet to follow up on the investigations.

As I came out, there was a call from Labour Room. There was CD, a 27 year old G3P2L2 with leaking since early morning. The duty nurse requested me to come fast as the abdomen looked abnormal. One look was enough to suggest that it was either a transverse lie or a Bandl’s ring had formed, the former more likelier than the latter. There was more in store. I did a per vaginal examination and to my horror, a good 2 inches of the umblical cord was hanging out of the cervix and it was pulsating well. The patient had started to contract and there were no membranes. I was not sure if the baby was alive. The nurse was sure she heard the fetal heart.

I took CD for an ultrasound abdomen. Thankfully, the baby was alive. The question was how much longer she would hold on. The only saving grace was that the baby being in a transverse lie, there was nothing putting pressure on the cord.

I rolled her straight from the ultrasound room to the theatre where a call from the laboratory put me in trouble. Her hemoglobin was only 6 gm%. I had no other choice but to operate immediately if I wanted a live baby. With a prayer that the Lord will protect the mother and the baby and very high risk consent from the bystanders, we went on with the surgery. The mother and the baby are doing fine. By evening, the bystanders had arranged couple of pints of blood.

There was more happenings going on elsewhere. Shazia, our community health staff was helping us take the delivery of a Nycocard reader in EHA Central Office in Delhi. The person from the company had called me just before the surgery on CD and had told me that they did get any intimation of the NEFT transfer of the required funds for the purchase of the machine. I explained that the transfer has been made and requested that the machine be handed over. I’m glad that the machine was given although the confirmation of the transaction of funds is yet to happen.

As soon as CD’s surgery was over, I went over and scanned a copy of the NEFT transfer slip and send it over. Later, there was a problem in the pharmacy as it turned out a batch of Ranitidine tablets were becoming semisolid like - almost  liquid-like. So, I had to officially intimate the suppliers as our requirements are quite voluminous.

I made my way to the OPD, where Angel was having trouble with a patient with hallucinations and delusions. The patient was quite poor. From the history, it was obvious that the patient was going into Schizophrenia. I told them of the option of going to Ranchi, but it was quite obvious that it was going to be difficult. So, I had to call up my friend, Dr Raja at Burrows Memorial Christian Hospital, Alipur and soon I had put in a plan of action for the patient and they were quite relieved. That’s telemedicine for us.

Soon, we had our next obstetric emergency. EE, a 34 year old G3P2L2 who had been in labour elsewhere had turned up in the OPD. She had an abdomen like a pear. We had a similiar patient couple of months back. It was obvious obstruction. The only question that remained was whether she had started to rupture. Once again, I was not sure about the baby’s status. The ultrasound showed a fine baby. I had to operate her.

She looked sure anemic. My only prayer was that she would be at least 8 or 9 gm%. She was 7 gm%. But the severity of obstruction she had made me to take a decision to go ahead with the surgery as soon as possible. After sending the relatives to somehow get hold of 2 pints of blood I took the baby in. Once I opened the uterus, I wished I had put in a midline vertical incision rather than a Joel Cohen Incision. The bladder had been pulled quite high up. I had to reflect the upper flap of the abdominal wall quite high to reflect the peritoneum down.

My prayers were answered when we delivered a live girl baby. She had a poor Apgar initially, but was well resuscitated by the theatre team. When I went in the evening to review her, she was bawling out. And oh my, the only time you feel so happy to see a child cry out.

I had staff from the hospital where EE was admitted for the last 3 days. It seemed that she was asked to go to a higher centre on Saturday night as the doctor had felt that the baby had not rotated properly and she could need a Cesarian Section – but the family had not taken it seriously. And having waited for quite long – they had taken a very high risk.

As soon as I finished surgery, Sr. Bharati, the Nursing Superintendent had news for me. Dr. Nandamani could hardly sit, leave alone work. He had told me that he was feeling quite sick in the morning and I had told him to take sick leave if he finds things difficult. Dr Nandamani had left OPD and there was quite a large crowd.

As usual, there was a bunch of tuberculosis patients, couple of patients with bronchial asthma, two patients with long duration of fever with typical features of dengue and a low platelet count whom I ultimately admitted.

However, I need to tell you about a patient who I felt so bad about. She was SD, a 65 year old lady with a swelling over her right cheek. It was obvious oral malignancy which was spread locally. There was nothing much I could do. As soon as I told the husband that he needed to take his wife to the Medical College under Banaras Hindu University, both of them started to cry. I asked them about their children. More tears rolled down their cheeks – there was so much of hopelessness in their eyes.

I told them that I’ll help them to obtain help in going. They sat down and talked for a long time. It seemed that their children were doing well. But, they had no time for the parents. I gave letters for them to give to the local government authorities so that they could request help.

Like the many malignancies which we have been seeing of late, most of these poor people have nowhere to go.

In between, we had a elderly lady with electrical burns. There was only about 10% of burns and most of it was quite deep. Since electrical burns could be quite deep such that it could involve even the bones, the patient was quite elderly and the family looked quite well off, I gave them the option of taking her to Ranchi which they promptly did.

By the time, we finished OPD it was 5:30 pm. As with each day, we had learnt quite a lot. There are concerns which I would share in my later posts especially about the prevalence of anemia which is responsible for quite a lot of morbidity and mortality in this part of the country.

I also realized that Dr Shishir, Dr Nandamani, Dr Angel and I had dealt with quite a number of sick patients whose management could have resulted in quite a number of complications and I acknowledge the grace of God in whatever we did during the day. My prayer is that our patients also realize the same in their lives.