Tuesday, September 4, 2012

A Justification . .. ...

I need to keep reminding myself on how I started off this blog . . . I've had many a person writing back to me  telling me how inappropriate it is to put many of my posts in the blogsphere. 

Very recently, after my post on the very unusual post about the rupture uterus, after I cross-posted it in a public healthcare site, I had someone ask me if it was appropriate to have posted it there. I thought it was appropriate . . . I don't mind if someone thought that it was inappropriate . . . 

About a week back, one of my staff told me that I belittle the region I'm in by portraying deficiencies of healthcare in the region by stuff I post. I asked him about what I should be posting. He told me he would think about it and let me know . . .  I've not heard from him ever since. 

Everybody loves to have beautiful romantic stuff posted . . . And it's not that I don't do that. 


Why do I write about cases of maternal deaths, near misses, tuberculosis cases etc. etc. 

It's because they are all so successfully treatable if not preventable to quite a large extent. 

The lady with the rupture uterus . . .  You should hear her story. 

We shall call her AAD. She had her first baby by Cesarian section for a reason about which she has no clue about. According to her after she was discharged after her Cesarian, nobody told her about not trying to deliver at home for her next deliver. Result . . . she did not bother to even do a routine antenatal care for her next pregnancy.

AAD started to have contractions early morning. The local village dai (traditional birth attendant) was called. She told the family that everything was fine and she should deliver by afternoon. Sometime mid morning, the dai felt that he was not progressing well and gave her four intramuscular injections . . . by our usual experience, it's pitocin. By afternoon, AAD had started to contract violently. It was excruciating pain. 

By around 3 pm, the family felt that she should take her to the district hospital. Whoever saw her at the district hospital was sure that the baby was doing well and she would deliver soon. She was there till around 7:00 pm, when they decided to move on. 

She reached us at around 9:00 pm. We did not need rocket science to find out that it was a rupture uterus. Per operatively, it was very evident that the rupture uterus had happened quite recently. The baby was a fresh still birth. 

I did not have any choice other than to do a tubal ligation (Family Planning) as the rupture was quite a bad one . . .  Like many of our previous stories, the husband would most probably abandon her for another woman who will be able to offer him more babies . . . 

The first time, when I told a similar story to one of my classmates, he told me that it was so unthinkable a story. But the fact remains that we have so many similar stories in our country and the world which are unfathomable to have occurred in an era when cutting edge medical science is looked upon with awe . . .

I've taken it up as a duty to bring to light such stories so that nobody who reads them will ever tell that they never knew there were such regions where such basic issues of healthcare were never taken care of and they could have played some role in alleviating the pain . . . .

That would bring me once again to the point of inviting more of my fellow healthcare professionals (rather nagging) to move out into needy areas of the country where your presence would end up saving lives and showing people that there is a God who cares . . . 

Sunday, September 2, 2012

RSBY Success Story . . . But . . .


On the 24th of last month, MDO, a 20 year old young man was searching for some thing in his house late in the night, when he was bitten by a krait on his hand. As is the prevalent practice, his relatives summoned a local faith-healer who assured them that everything was alright.

However, as time passed, the father realised that something was amiss. MDO was not able to breathe properly and was looking very sleepy.

NJH, being very near to his home and one of his cousins being a chowkidar in the hospital – the family rushed MDO to NJH.

On arrival at NJH, Dr Johnson attended the call. MDO was hardly breathening and was bluish all over. There was no response to stimuli and his pupils were mid-dilated and hardly reacting. MDO was intubated and was put on the mechanical ventilator. The relatives were explained about the very small chance of survival. It was about 1:00 am of 25th August. 

Meanwhile, our chowkidar, Mr. Jamuna who was MDO’s cousin told us about the RSBY Smartcard (Rashtriya Swasthya Bima Yojana) the family had. It was brought immediately and was promptly blocked for treatment of snake bite.

It was only recently we were having a discussion of snake bites being covered under RSBY as there was a major increase in costs of Anti-Snake Venom (ASV).

Since, we were yet to come to a conclusion on the increase in ASV costs, we decided to treat him fully under RSBY.

By the 25th morning, when I came for rounds, MDO’s pupils were fully dilated and fixed. There was no reaction till about 26th afternoon.

He was in the ventilator for 80 hours. And intubated for 104 hours. 120 hours of Acute Care admission. . . 30 B-type oxygen cylinders . . . 20 ASVs - the cost of which alone is 13000 INR

MDO is getting discharged today. The problem was that his total bill had come to a whopping 45000 INR and RSBY was going to pay us 10500 INR.

MDO with his father
We’re not sure on how to approach this. The family is ready to pay us 7500 INR more. But, as per RSBY policy we are supposed to be giving cashless service. I’ve sent a mail to our Insurance Providers explaining about our predicament. I hope that they would respond positively.

The interesting part is that we have 3 more patients in the ward with krait bite. And all of us are in some part of their ventilatory support . . . I’m glad that we have 2 ventilators . . . But still, we’ve to refuse all patients who could end up needing a ventilator since yesterday . . .  eclampsias, snake bites, severe pneumonias etc . . .

The recent increase in cost of ASV make it quite difficult to treat snake bite victims under any protocol of snake bite management under RSBY. I hope that the concerned authorities would take note and do the needful . . . 

(Consent to publish the photograph and the story has been obtained)

Images of an unusual Rupture Uterus . . .

(This post is purely of medical academic interest and contains snaps which could be offensive. 
User discretion strongly advised)


I hope you remember this image from my earlier post. This is RD's baby who came in with a hand prolapse after she was diagnosed earlier with a transverse lie. It was only after Dr. Titus read the post that he told me that I had forgotten to mention that RD had a previous Cesarian. 

I did not know that since I was not directly involved with RD's management. 

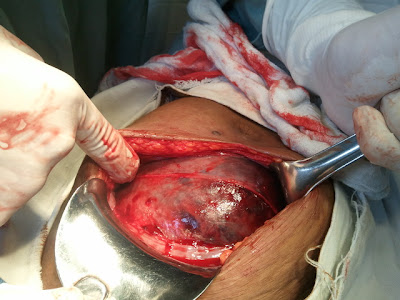
Talking of previous Cesarian Section, about a week back we had another patient with a previous Cesarian who came in with a Rupture Uterus. Below are the snaps taken per-operatively. Kindly excuse for the messy background as we were in quite a hurry to finish the surgery as the patient was quite sick. 

Area of rupture which was along the left lateral wall of the uterus, into the broad ligament.

Another view of the ruptured area after we started to suture it up. 

Hematoma from the ruptured region which extended along the mesosalpinx

The avulsed round ligament . . .

The surprise . . . The intact uterine scar of the previous Cesarian section which was marked very clearly by the bleeding which tracked along the suture line. We double checked it to ensure that there was no breach of the incision.  

It was quite amazing that the uterine incision of the previous Cesarian section was intact and the rupture was through the lateral wall into the broad ligament. One can only imagine the pain that the lady went through. 

However, by God's grace, she had an uneventful post-operative period and was discharged yesterday.

Thursday, August 30, 2012

Photo Post . . . 30th August

Few snaps from our day to day work . . .

Ring enhanced lesion in a young boy who had come with seizures. Something we see very regularly. After the CT Scan, he was seen elsewhere and started on anti-tuberculosis medication . . . 
We had thought pre-operative that this lady had a rupture uterus. However, on opening, we found that it had not yet ruptured. . . but the lower segment was battered into a mass of 'minced flesh' enclosed by the peritoneum outside and the amniotic membranes inside. I wonder if there is a name for that yet . . . If there isn't, we shall coin one . . . 


Massive pericardial effusion. We found malignant cells in the fluid which we got following a pericardial tap.
The lady passed away after she was referred to Ranchi. 

Steven Johnson's syndrome following Tab Septran. There was candidiasis too. . . 

Pine tree on the way to Netarhat . . . Something I did not expect in Jharkhand

An Allwyn refrigerator. Fond memories. . . I wonder if anybody remembers this refrigerator company . . .

Artemesia plant . . . From which we get Artemesin derivatives . . .  

Our new generator . . .  


Friday, August 24, 2012

The Bengal Monitor . . . Questions remains

The last time, I had done a post about the possibility of the bite of a Bengal Monitor being fatal, I had quite a few mails from people who told me that it is not known to be venomous. But the victim, SK ultimately succumbed. 

Well, yesterday, I had a young boy who came with a confirmed bite of a Bengal Monitor. Similar to the case with SK, I confirmed the offending creature by showing the victim snaps of the reptile from wikipedia. The snap he identified is the one below - 


Below is the snap of the bite site.


The bleeding from the gums.


The creature had bit him at around 4 in the evening. And he started to vomit blood at around 4:30 pm. He was at NJH by 5:00 pm. He was bleeding from his gums. Clotting time was more than 20 minutes.

Well, there are things about which we still do not have any idea. We gave an option to go to a higher centre, which the parents accepted. We have got the family's phone number. Shall post if we come to know anything . . .